Melasma Treatment: What Works, What to Avoid, and How Peels Fit
There is no single best melasma treatment. The approach that works for most people combines strict sun protection with medication, and sometimes adds in-office procedures such as chemical peels or lasers. The American Academy of Dermatology says it usually takes 3 to 12 months of following a plan to see results. This guide explains each option, where peels fit, who needs extra caution, and how to keep patches from returning.
TL;DR
- Daily, tinted, broad-spectrum sunscreen is the foundation. Without it, no other treatment holds.
- Prescription lighteners (hydroquinone, tretinoin, azelaic acid) are the usual first step, used under a clinician’s guidance.
- Chemical peels and lasers are add-ons, not stand-alone cures, and need careful selection on medium and darker skin tones.
- Expect months, not weeks. Melasma tends to relapse with sun, heat, hormones and skipped maintenance.
- A medical evaluation first tells you which pigment problem you have and which tools fit your skin.
Table of Contents
- What melasma is and why it is stubborn
- Step one: sun and light protection
- Step two: topical medications
- Where chemical peels fit
- Other in-office options
- How long melasma treatment takes
- Melasma on darker skin tones
- Perspective
- A practical routine you can start today
- Treatment in the Bay Area with LA ViE MD
- What to ask before any melasma procedure
- FAQ
- Sources
What melasma is and why it is stubborn
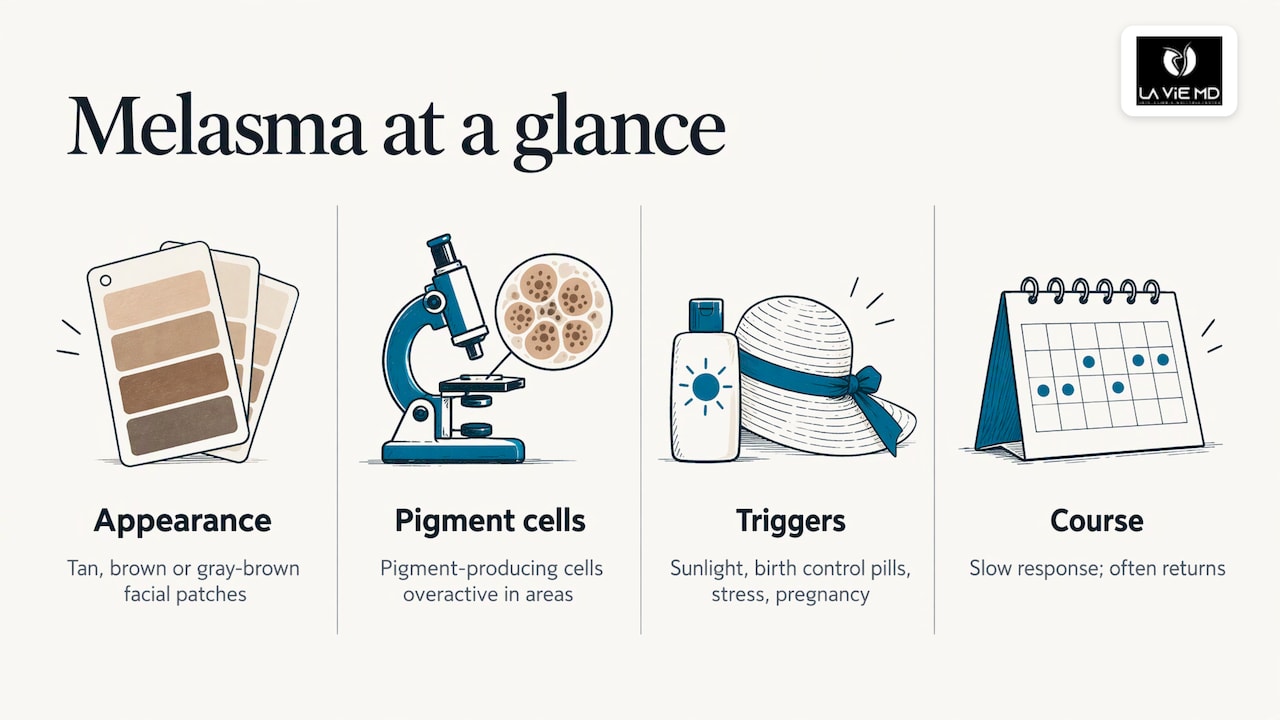
Melasma shows up as tan, brown or gray-brown patches, most often on the cheeks, forehead, upper lip and nose. It is a pigment disorder, which means your pigment-producing cells are overactive in certain areas. It is not dangerous, but it can be frustrating because it responds slowly and often returns.
The common triggers are well documented. The AAD notes that sunlight, birth control pills and stress can bring melasma on, and that sun protection helps prevent it from coming back. Hormonal shifts such as pregnancy are also linked to flare-ups.
Because other dark spots look similar, it helps to know what you are treating. Sun spots and melasma need different strategies. Our comparison of melasma versus sun spots explains how to tell them apart.
Step one: sun and light protection
Every guideline starts here, and with good reason. The AAD says sunlight can darken existing melasma and cause new patches.
What to look for in a sunscreen:
- High SPF with broad coverage. The 2024 International Society of Dermatology guideline summary recommends SPF 50+ with UVA and UVB protection plus visible-light protection.
- Iron oxide tint. The same guideline prefers pigmented, iron oxide-based sunscreens. AAD self-care guidance explains that visible light can worsen melasma, especially in people with darker skin tones, and suggests a tinted sunscreen with iron oxide and SPF 30 or higher.
- Reapplication and shade. A hat and shade on sunny Bay Area days matter as much as the product. Driving and window light count too.
If you do only one thing from this article, make it a daily tinted sunscreen. Every treatment below works better on protected skin.
Step two: topical medications
Creams are where most plans begin. According to the Merck Manual, skin-lightening creams can combine hydroquinone, tretinoin or a corticosteroid, and azelaic acid can be used instead of or alongside them. A review of topical therapy discusses a triple combination of hydroquinone, retinoic acid and a corticosteroid as a first-line choice.
| Option | What it does | What to know |
|---|---|---|
| Hydroquinone | Lightens existing patches | Use under a doctor’s guidance; the Merck Manual warns long-term use can sometimes cause a permanent form of hyperpigmentation |
| Tretinoin | Speeds skin turnover so pigment sheds | Can irritate; a clinician sets strength and schedule |
| Azelaic acid | Alternative or add-on lightener | Often better tolerated |
| Corticosteroid | Calms irritation in combination formulas | Prescribed in combination products |
| Oral tranexamic acid | Adjunct therapy in some plans | Prescription only; the ISD summary lists it among adjuvant options |
The point of the table is that none of these should be improvised. Strength, duration and breaks all matter, and a clinician can adjust them as your skin responds.
Where chemical peels fit
If you searched for a chemical peel for melasma, here is the honest picture. Peels are an add-on. The ISD guideline describes them as adjuncts that speed epidermal turnover and clear melanosomes, meaning they help shed pigment-laden cells. The Merck Manual says glycolic acid or trichloroacetic acid (TCA) peels may be tried when creams do not lighten melasma.
What the evidence shows
A randomized trial from India found lower mMASI scores (a melasma severity measure) after 15% TCA peels, and after a combination of 15% TCA, 15% phenol and 2% glycolic acid. That supports peels as a useful tool within a plan. It does not mean one peel clears melasma, and results depend on skin type, peel choice and how well the skin is protected afterward.
Why peel choice matters
The ISD summary points out that glycolic acid can be more irritating than hydroquinone alone and carries a small risk of postinflammatory hyperpigmentation, particularly on dark skin. It also advises avoiding medium-depth peels. In practice that means superficial, gentle, carefully spaced peels, often paired with a prescribed home regimen and skin priming beforehand.
Irritation is the enemy in melasma. A peel that inflames the skin can darken it. That is why a medical evaluation, a patch approach and a conservative start matter more than the specific acid.
Peels versus lasers
Both are options, and they suit different situations. If you are weighing resurfacing choices, our guide to choosing between a chemical peel and laser walks through the trade-offs. Lasers and light devices are listed in the ISD guideline among adjuvant therapies, and the Merck Manual notes lasers are also used. Because heat can aggravate melasma, device settings and skin type need professional judgment.
Other in-office options
Melasma plans are often built in layers. Depending on your skin, a clinician may combine:
- Medical-grade facials such as HydraFacial for gentle exfoliation and hydration between stronger treatments.
- Microneedling, which is a skin-renewal option some plans include.
- Pigment-targeting lasers, selected by skin tone and the depth of pigment.
- Medical-grade skincare to keep a home routine consistent.
At LA ViE MD, our skin rejuvenation treatments and laser procedures include options such as HydraFacial, microneedling and PicoWay for melasma and pigmentation. Which of them, if any, belongs in your plan is decided at a consultation, not in advance.
How long melasma treatment takes
Plan on months. The AAD says that when you follow your treatment plan, results usually appear between 3 and 12 months. Many people see early fading in the first couple of months, but the deeper patches take longer.
A realistic timeline looks like this:
- Weeks 0 to 4: start sunscreen, a home regimen and any prescribed creams. Skin may feel dry.
- Months 1 to 3: if your plan includes peels or other procedures, they are typically spaced out so skin can recover in between.
- Months 3 to 12: gradual lightening and evening of tone, with adjustments as needed.
- Ongoing: maintenance, because relapse is common.
The ISD summary lists sun exposure, skipped maintenance, lack of broad-spectrum protection, hormonal therapy and pregnancy as factors tied to higher relapse risk. Treat maintenance as part of the treatment, not an optional extra.
Melasma on darker skin tones
Melasma is common across skin tones, and medium to deep skin brings extra considerations. Visible light is a bigger factor, which is why iron oxide tints matter. Skin is also more prone to postinflammatory hyperpigmentation after irritation, so gentler peels, conservative laser settings and slower progress are the norm. Ask any provider how they adjust treatments for your skin tone and what they do if a patch darkens.
Perspective
Melasma is one of the conditions where patience and personalization beat intensity. We see people arrive having tried every brightening serum online, and the common thread is usually inconsistent sun protection or products that irritate the skin more than they help.
At LA ViE MD, we start with a physician-supervised assessment of your skin, your history and your triggers, including hormones, medications and sun habits. Then we build a custom plan. That may mean a medical-grade home routine, a gentle facial or peel series, or a pigment-focused laser such as PicoWay, each chosen for your skin type and spaced so your skin can recover.
Our approach is designed to be conservative and steady. Melasma rewards a plan you can actually follow for months, with a clinician adjusting along the way.
Dr N
A practical routine you can start today
While you plan a visit, these steps are safe starting points for most people:
- Wear tinted, iron oxide sunscreen every morning and reapply when outdoors.
- Add a wide-brimmed hat for driving, hiking and weekend errands.
- Keep your routine gentle. Skip harsh scrubs, hot tools and anything that stings.
- Note your triggers: new medications, hormonal changes, pregnancy or heavy sun periods.
- Take photos in the same light every month to see slow progress.
If you are pregnant, planning pregnancy or on hormonal medication, tell your clinician before starting any prescription lightener, since options differ.
Treatment in the Bay Area with LA ViE MD
We treat pigment concerns at our East Bay and South Bay locations, under the supervision of Dr. Neetu Nebhwani, a board-certified Internal Medicine physician with over ten years of experience. Your visit starts with a consultation, and your plan is built around your skin concerns and goals. Our Livermore hyperpigmentation page and Los Gatos hyperpigmentation page describe what we offer locally.
To see the laser options in one place, visit our laser procedures page, or book a consultation through our site to talk through your patches.
Bring a list of the products you currently use and any medications, so the plan fits what your skin has already been through.
What to ask before any melasma procedure
Whichever provider you choose, a good consultation covers the same ground:
- What is my diagnosis, and could any patches be something other than melasma?
- Which treatment do you recommend first, and why for my skin tone?
- How many sessions are typical, and how far apart?
- What will my skin look like afterward, and for how long?
- How will we handle sun protection and maintenance?
- What happens if a patch gets darker?
Clear, specific answers to these are a sign of careful, individualized care.
FAQ
What is the best treatment for melasma?
There is no single best option. The AAD says the most effective approach often combines sun protection with medication. Peels, lasers or other procedures may be added depending on your skin and how patches respond.
How do you get rid of melasma fast?
Melasma does not clear quickly. Results usually take 3 to 12 months, according to the AAD, and aggressive shortcuts can irritate skin and darken patches. The fastest reliable path is daily tinted sunscreen, a prescribed regimen and consistent follow-up.
Is a chemical peel good for melasma?
Superficial peels can be a helpful add-on when creams alone are not enough. Guidelines describe peels as adjuncts, and they advise avoiding medium-depth peels. Skin type matters, because irritation can cause pigment to darken, especially on darker skin.
Can melasma come back after treatment?
Yes. Sun exposure, hormonal therapy, pregnancy and skipped maintenance all raise the risk of relapse. Ongoing sunscreen use and a maintenance routine reduce it.
Sources
- Melasma: Diagnosis and treatment, American Academy of Dermatology
- Melasma: Self-care, American Academy of Dermatology
- Melasma, Merck Manual Consumer Version
- Melasma Treatment: ISD 2024 Guideline Summary, Medscape
- Comparative efficacy of chemical peeling agents, PubMed Central
- Topical treatment of melasma, PubMed Central